Lessons from Singapore Airlines · for dermatology practices
Split the Team Hour Before the Month Starts. Then Keep It, Even in Good Months.
A Singapore Airlines manager once described a 40-30-30 rule: 40% of resources to training people, 30% to reviewing how the work is done, and 30% to new ideas. All three pay off later, and a busy day pays off now. Your clinic can give each one its share before the month begins, and then keep it.
What you’ll take away
- The problem
- Practice, fixing what keeps breaking and staff ideas all pay off later. A full schedule pays off today, so the team hour is often the first thing a month gives away.
- What to remember
- Decide the split before the month starts: the biggest share for practice, a share to fix one process, a share for one staff idea. Then keep it, in busy months and good ones.
- What to do differently
- Block one paid team hour before next month’s booking opens, and post its three shares. If a patient urgently needs the time, move the hour within the month. Never cancel it.
30-Second Summary
- Under pressure, the work that pays off later is what gets cut. Management researchers call it the capability trap: improving the work gives the more lasting gain, but only after a delay, so a short push to work harder turns into the everyday way of working.1
- A Singapore Airlines manager described a split. In a teaching case, a senior manager in charge of staff development described the airline’s 40-30-30 rule: 40% of resources to training people and keeping them energized, 30% to reviewing how the work is done, and 30% to new products and services.2
- Separate records show the training and the ideas. In 2007-08, staff sent in nearly 6,000 ideas, and a case study reports that every one was evaluated.3 In its report for the year to March 2026, the company says employees of Singapore Airlines and Scoot, its low-cost airline, averaged 76 hours of training, and Scoot sets aside two hours each Thursday for its office staff to learn.4
- Keep it when things go well. After DuPont’s maintenance program paid off, a team member warned that people would be taken away once the problems fell, and company cost-cutting then weakened the program.1 A software team’s protected quiet time had faded within months, and old habits were back.5
- In your clinic: before the month starts, block one paid team hour and split it on purpose: 24 minutes of practice, 18 minutes to fix one process, 18 minutes for one staff idea. If a patient urgently needs the time, move the hour within the month. Never cancel it.
The Problem
What Goes Wrong When Improvement Waits for a Free Hour
Every team has work that pays off later: practicing a skill before it is needed, fixing a step that keeps going wrong, trying out a better idea. Every team also has a schedule that pays off today.
Management researchers Nelson Repenning and John Sterman studied improvement programs in manufacturing, product development and other companies, and named what happens next the capability trap. Time spent improving the work gives the more lasting gain, but it pays off only after a delay. So when pressure rises, organizations cut improvement time and push people to work harder instead.1 “What starts as a temporary emphasis on working harder quickly becomes routine,” they wrote.1
In their study, successful improvement programs were the exception. In most organizations improvement stalled, and even where early results came, cost and schedule pressures drained resources away from it.1
One of their examples was maintenance at DuPont. In 1991, the company’s own benchmarking study found that it spent 10 to 30 percent more on maintenance than the industry’s leaders, for each dollar of plant value, while its plants were up and running some 10 to 15 percent less of the time.1 More spending, less running.
Hospitals show a similar pattern. Watching nurses at nine hospitals, Anita Tucker and Amy Edmondson found that for 93% of problems, nurses did what it took to keep caring for the patient and left the cause in place. They tied this partly to staffing designed with no slack time.6 Nobody decides to stop improving. The time just never gets set aside.

The Exceptional Solution
Singapore Airlines’ Answer: A Share for Each Kind of Work
Business-school researchers Jochen Wirtz and Loizos Heracleous have written a teaching case on how Singapore Airlines manages its people. They describe five connected parts of its people strategy: strict selection, heavy investment in training, strong service teams, empowered frontline staff, and rewards and recognition.2
In the case, they quote a senior manager in charge of staff development about a program called Transforming Customer Service. It brought in staff from five parts of the operation, among them engineering, cabin crew and ground services.2 Inside that program, she said, sits a 40-30-30 rule covering people, processes and products.2
Here is how she described the three shares, and what the record shows:
40% to people. The airline, she said, focuses 40% of its resources on “training and invigorating our people.”2 The case describes new cabin crew starting with an intensive 15-week course.2 A former chief executive, Cheong Choong Kong, put it this way: to the company, “training is forever,” at any age.2
30% to processes. Another 30%, she said, goes to “reviewing processes and procedures.”2 Heracleous and Wirtz describe individual departments running their own continuous improvement, paid for from their own budgets.3
30% to new ideas. The last 30%, she said, goes to coming up with new products and services.2 A small product innovation department, staffed by people who rotate in every two to three years, handles the big projects.3 Alongside it, a staff suggestion scheme called Staff Ideas in Action had been running for nearly 30 years. Heracleous and Wirtz report that in 2007-08, staff across the group sent in nearly 6,000 ideas for cutting costs and working more efficiently. Every one was evaluated. More than 40% were put to use.3
A fixed place on the calendar. Scoot, the group’s low-cost airline, introduced SPARK Time, which reserves two hours on Thursdays for its office staff.4 The block is for self-directed learning, knowledge sharing and conversations with leaders.4
Recent figures come from a separate source and a different time. In its sustainability report for the year to March 2026, the group says employees of Singapore Airlines and Scoot averaged 76 hours of training, and cabin crew averaged 85.4
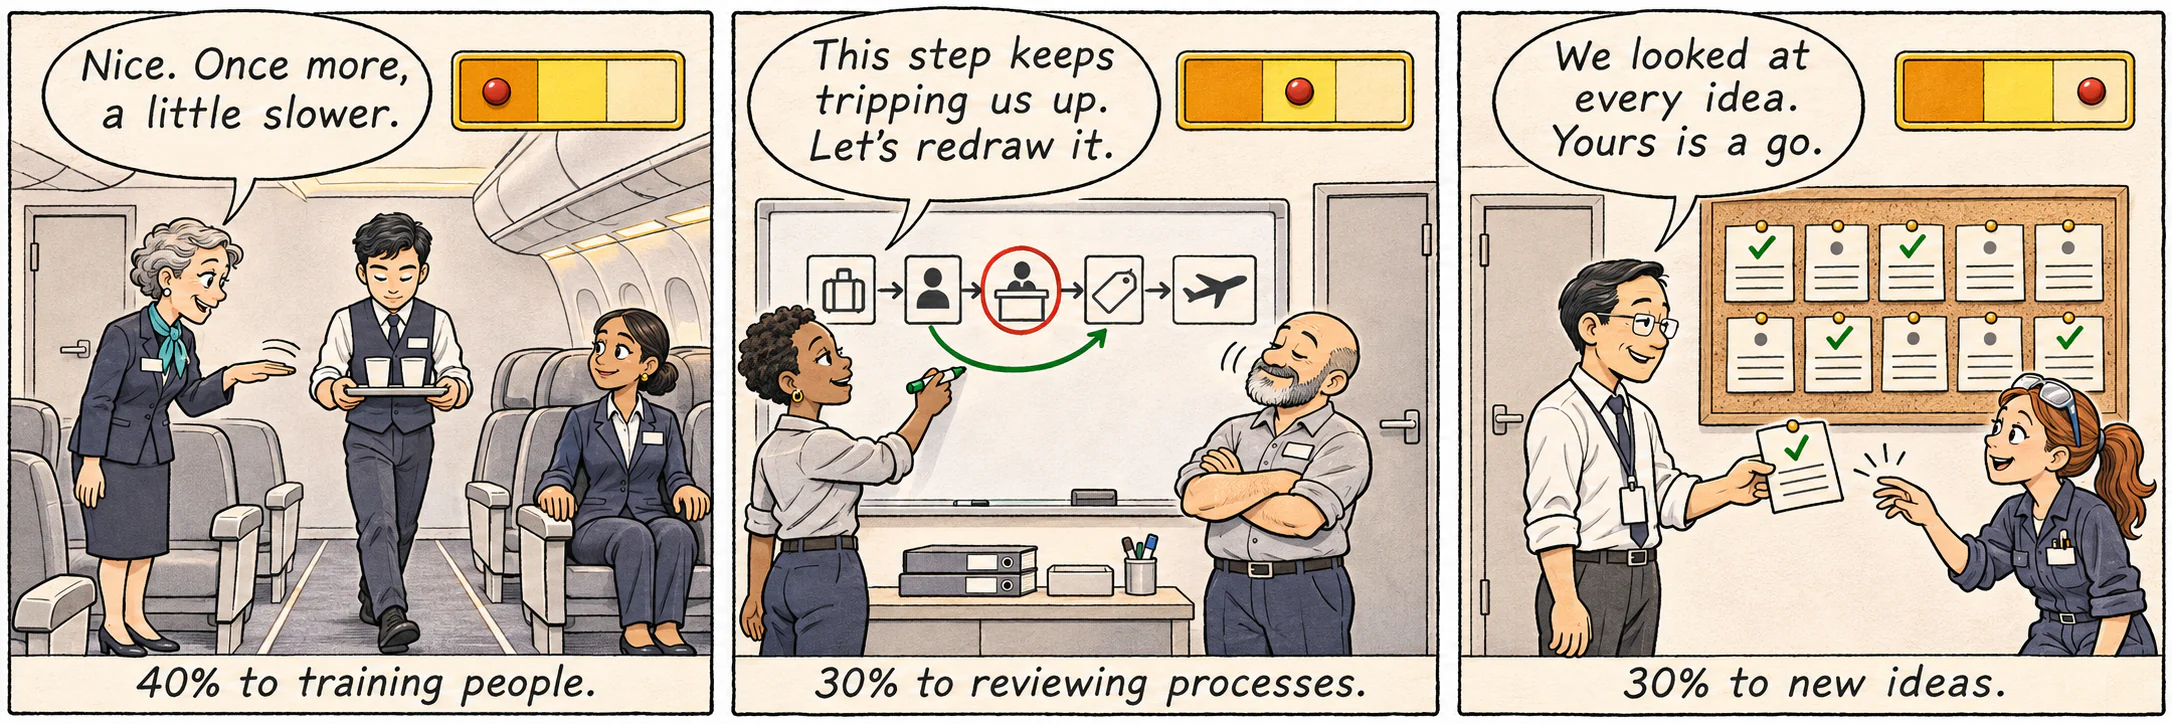
The ProblemThree kinds of work pay off later: practice, fixing a process and new ideas. The schedule pays off today.
The Mediocre ApproachWait for a free hour
Action
Fit it in when things calm down.
- Practice, repairs and ideas wait for a quiet week
- Every spare hour goes to today’s work
The Exceptional ApproachSingapore Airlines’ answer: a share for each
Action
Name the shares. Give the time a place.
What Keeps It Going
The percentages matter less than what surrounds them:
Named. Three kinds of work that pay off later, each with its own share.2
On the calendar. Scoot’s block comes around every Thursday.4
Evaluated. The case study reports that every idea in the staff scheme was evaluated.3
A team that waits for a free hour leaves its future to whatever time is left over. The manager’s rule gave each kind of work its own share, and Scoot gave learning a fixed day. A share that is already named doesn’t have to win a new argument every busy day.
The mechanism
Why It Works
A split sounds like arithmetic. It works because each part does a different job: deciding ahead settles the argument once, practice builds the skill before the hard moment, a fix-it share gives the lasting repair a time, an answer gives every idea somewhere to land, and holding on in good months keeps what you gained.
Tap or click a card to see why it works.
-
Decide once, ahead of time.
Work that pays off later needs its time promised first.1
Why it works
- Today outbids later. Working harder pays off right away. Improving the work gives the more lasting gain, but only after a delay.1
- Pressure cuts it. Under pressure, organizations cut improvement time, and the push to work harder becomes routine.1
- A rule ends the daily argument. A share that is already decided doesn’t have to beat a full schedule every morning.
-
Practice gets the biggest share.
People first: 40%, the largest of the three.2
Why it works
- The biggest of the three. In the manager’s rule, training people got 40%, more than either other share.2
- Training never stops. A former chief executive said that at the company, training never ends, whatever a person’s age.2
- Training changes what people do. A review that pooled studies of workplace training found a medium-to-large average gain in how people behaved on the job afterward.7
-
Give the fix its own time.
Or the workaround wins.6
Why it works
- On the list from the start. The manager named a review of how the work is done as one of the three shares.2
- Workarounds are the default. Nurses kept care going around 93% of the problems researchers saw, and only 7% of their responses got to the cause, partly because staffing left no slack time.6
- Run where the work is. At Singapore Airlines, departments run their own continuous improvement from their own budgets.3
-
Ask for ideas, and answer every one.
Every idea evaluated; more than 40% used.3
Why it works
- A standing invitation. Staff Ideas in Action had been running for nearly 30 years.3
- Every idea was evaluated. Heracleous and Wirtz report that all of the nearly 6,000 ideas from 2007-08 were evaluated. More than 40% were put to use.3
- Fresh eyes on the big changes. People rotate into the small product innovation department every two to three years.3
-
Why it works
- A warning from inside. After DuPont’s maintenance program paid off, a member of its team warned that once the problems came down, people “will be taken away from the effort,” and the problems would come back.1
- Then it happened. Company-wide cost-cutting brought downsizing that weakened the program and limited its growth.1
- Protected time fades. A software team’s quiet mornings raised the share of engineers who rated their own productivity above average to 59%, then 65%. Months later, the engineers had gone back to their old work patterns.5
The evidence
The Results, and Where Else It Works
Singapore Airlines reports its training in hours, and researchers who studied it counted what became of staff ideas.3, 4 Health care has tried protected time too. In a Welsh pilot that funded protected learning days for community pharmacists, participants suggested booking the time in pre-scheduled slots.8 And in outpatient clinics, teams that rehearsed rare emergencies where they work found problems they could fix.9
The first three cards come from the airline group; the last two come from health care. Flip each card for the result and the lesson to take home.
Tap or click a card to flip it.
-
76 hours of training per employee, on average, at Singapore Airlines and Scoot in the year to March 2026
- Who counted: The company, in its sustainability report for the year to March 2026.
- What was counted: Training hours for each employee, averaged over the year.
Exceptional results4
76 hours of training per employee, in the year to March 2026
- Cabin crew averaged 85 hours.
- The count covers Singapore Airlines and Scoot.
Valuable lesson: Give practice real time, and count the hours.
Source: Singapore Airlines Sustainability Report FY2025/26 · evidence row 4
-
Over 40% of nearly 6,000 staff ideas put to use at Singapore Airlines in 2007-08
- The ask: Staff sent their ideas to a scheme called Staff Ideas in Action.
- What the case reports: Every idea was evaluated.
Exceptional results3
More than 40% of staff ideas put to use, in 2007-08
- Staff across the group sent in nearly 6,000 ideas in 2007-08.
- The case study reports that every one was evaluated.
- The ideas aimed at cutting costs and working more efficiently.
Valuable lesson: Ask for ideas on a schedule, and tell each person what happened to theirs.
Source: Heracleous and Wirtz, J Appl Behav Sci 2014 · evidence row 3
-
2 hours every Thursday, set aside for office staff at Scoot, the group’s low-cost airline
- The block: A standing two-hour slot, the same day every week.
- The use: Self-directed learning, knowledge sharing and conversations with leaders.
Exceptional results4
2 hours a week blocked every Thursday for Scoot’s office staff
- Scoot calls it SPARK Time.
- The block is for learning on your own, sharing what you know and talking with leaders.
Valuable lesson: Give protected time a fixed day and hour, like an appointment.
Source: Singapore Airlines Sustainability Report FY2025/26 · evidence row 4
-
609 studies of health-care trainees who practiced on simulators, pooled in one review
- The practice: Trainees rehearsed skills on simulators.
- What was compared: Their skills, against trainees with no such training.
Exceptional results10
Large skill gains for health-care trainees who practiced on simulators
- Their skills grew far more than with no such practice.
- The review measured the trainees’ own skills.
Valuable lesson: Rehearse the hard moment before it is real.
Source: Cook et al., JAMA 2011 · evidence row 10
-
40 safety concerns found when teams in 26 outpatient clinics rehearsed emergencies in their own clinics
- The practice: Teams rehearsed chest pain and a severe allergic reaction where they work.
- What turned up: Problems in the clinics themselves, which were then addressed.
Exceptional results9
40 concerns found during in-clinic rehearsal, then addressed
- Staff reported gains in knowledge, confidence and skills.
- The rehearsals turned up problems the clinics then addressed.
Valuable lesson: Rehearse in the real room, and fix what the rehearsal turns up.
Your dermatology clinic
Bringing It Home to Your Dermatology Clinic
Your clinic has its own work that pays off later: the hard phone call nobody has practiced, the supply that keeps running out, the good idea a scheduler mentioned once. It has its own rush, too. Researchers who followed 11 nurses through their shifts at six US hospitals counted an average of 8.4 work-system failures in every 8-hour shift, most often with medications, orders, supplies, staffing or equipment.11 On a day that full, the workaround gets done and the fix waits.
Start with one hour: the practice manager blocks one team hour for next month in the scheduling system before booking opens, the same way a patient appointment is blocked. It is paid work time for every role, including hourly staff.
Split it before the month starts: borrow the airline manager’s proportions. Of 60 minutes, 40-30-30 is 24 minutes of practice, 18 minutes to fix one process and 18 minutes for one staff idea. Post the split with its three topics, so everyone knows what the hour is for.
Practice, 24 minutes: rehearse one hard moment before it is real. Schedulers practice, in pairs, the call to a patient whose surgery date has to move, including the clinic’s rule that any move of a skin-cancer surgery date goes first to the nurse, who has the surgeon approve the new timing before any date is offered. Or the nurse walks the team through the clinic’s written emergency protocol at the procedure chair. Small studies of rehearsal inside outpatient clinics, from an allergy clinic to endoscopy and hysteroscopy units, report gains in staff confidence or knowledge, and the allergy clinic’s rehearsal also exposed gaps in its process that were then resolved.12, 13, 14 Rehearsals use made-up scenarios, never a real patient’s details, follow protocols a clinician approved, and add to required certification, never replace it.
Fix one thing, 18 minutes: pick one process that failed this month, such as liquid nitrogen running out before Friday clinic or a form that keeps turning up missing. Agree on one change, one owner and one start date. Anything that could harm a patient isn’t saved for the hour: the responsible clinician handles it the same day, and the hour is for the lasting fix. A change that touches a clinical step needs the medical director’s sign-off before it starts.
One idea, 18 minutes: open by reading last month’s ideas and what happened to each: yes, not now, or no, and why. Then choose one new idea to try. The practice manager approves the logistics. Any message to patients about eating, medications, wound care or preparation needs a clinician’s sign-off before it is sent.
Who keeps it: the practice manager owns the block. The lead physician’s part is to book nothing into it and to show up for it. If a patient urgently needs that time, the patient comes first, and the practice manager moves the hour to another slot in the same month. Good months count too: that is when the hour looks easiest to give back.
Here’s how that plays out in two everyday moments. Each one starts with the problem, follows the mediocre approach to its outcome, then rewinds to the same moment for the exceptional approach: the time, kept.
Example One: The Team Hour That Went to Two Skin Checks
- The Problem
On the 24th, the practice manager is building next month’s schedule. The lead dermatologist has two routine skin checks to fit in, and the only open time is Thursday’s team hour, already posted with its three shares. Its fix-it share is set for the liquid nitrogen that ran out twice this month. She asks to book the skin checks there, just this once.
 Doctor:Two skin checks, no openings that week. Can we use Thursday’s team hour?Practice manager (thinking):That would make three months in a row.
Asked before the month starts. The hour is still on the calendar with its three shares posted, so keeping it costs the least right now. - The Mediocre ApproachThe action
 Practice manager (thinking):It’s only one hour.Practice manager:Okay. We’ll skip it, just this once.
Given back. It’s one hour, and the doctor asked. The team hour comes off the calendar, and the nitrogen fix waits again. - The Mediocre ApproachThe poor outcome
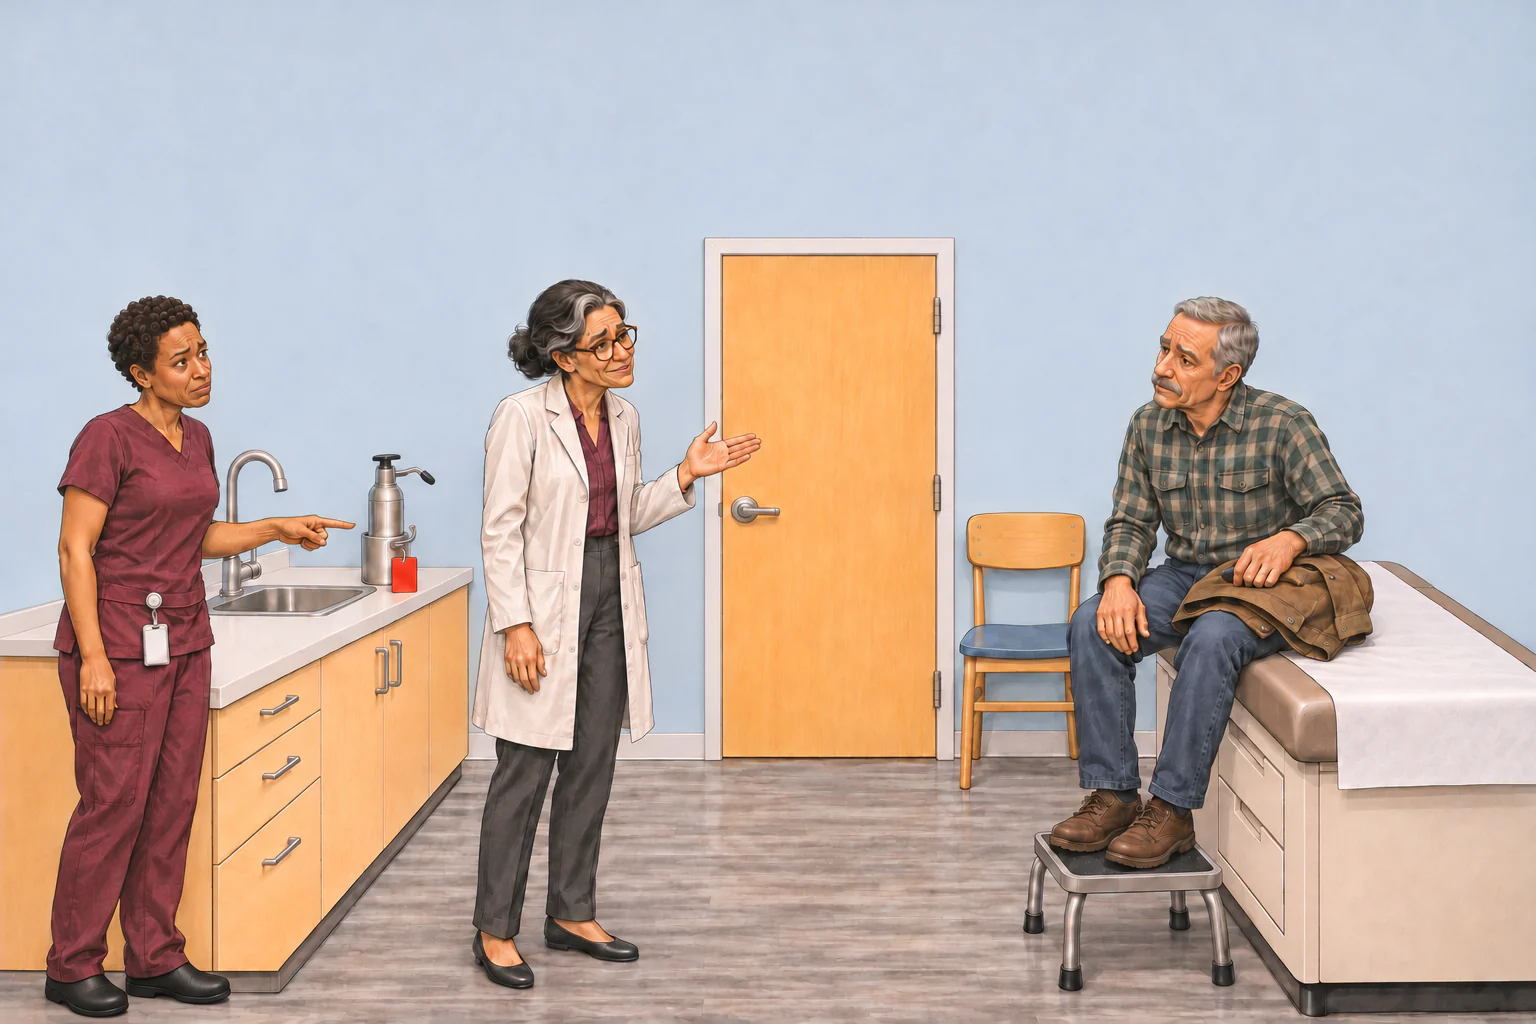 MA:The canister’s empty. So is the tank.Doctor:Empty again? I’m so sorry. We’ll rebook you.Patient (thinking):I took the afternoon off for this.
Three weeks later, Friday afternoon. The fix never got its 18 minutes. The liquid nitrogen is out again, so a patient booked for freezing treatment has to come back next week. Rewind. Same schedule, same request, same moment. This time, the hour is kept.
- The Exceptional ApproachThe action: keep the time
 Practice manager:That hour is booked, like a patient. Can they take the first openings the week after?Doctor:Yes, they’re routine. Keep the hour. I’ll be there.
Kept, like a patient. The doctor confirms the skin checks are routine, so they take the next two openings, and the doctor backs the hour. - The Exceptional ApproachThe exceptional outcome
 MA:Full. We check it every Wednesday now.Patient:Great. Let’s get it done.
Three weeks later, Friday afternoon. In its 18 minutes, the team agreed on one fix: the MA lead checks the nitrogen every Wednesday and reorders below a marked line. Today the canister is full.
Example OneAt a glance
The ProblemBuilding next month’s schedule, the practice manager is asked to book two routine skin checks into Thursday’s team hour, just this once. Its fix-it share is set for the liquid nitrogen that keeps running out.
The Mediocre ApproachGive the hour back
Action
Skip it, just this once.
- “Okay. We’ll skip it, just this once”
- The team hour comes off the calendar, and the nitrogen fix waits
Poor outcome
The same failure, again.
- Three weeks later, the nitrogen runs out on a Friday afternoon
- A patient booked for freezing treatment has to come back next week
The Exceptional ApproachThe hour kept: booked like a patient
Action
Keep the hour, and find another slot.
- “That hour is booked, like a patient”: the doctor confirms the skin checks are routine and can take the next openings
- The doctor backs it: “Keep the hour. I’ll be there”
Exceptional outcome
Fixed once, in 18 minutes.
- The MA lead checks the nitrogen every Wednesday and reorders below a marked line
- On Friday afternoon the canister is full, and the treatment goes ahead
Example Two: “Nothing’s Gone Wrong in Months”
- The Problem
The team hour has just started in the break room. Its first 24 minutes are for practicing one hard call: telling a patient that a skin-cancer surgery date has to move. It has been a smooth month, and a scheduler asks to skip the role-play.
 Scheduler:Nothing’s gone wrong in months. Can we skip the role-play?Front-desk lead (thinking):She’s right. We’ve been fine.
Asked in the first minute. The shares are on the whiteboard and the timer is ready. A good month is when practice looks least needed. - The Mediocre ApproachThe action
 Front-desk lead:Fair enough. We know this stuff. Catch-up time.Scheduler (thinking):Phew. No role-play.
Practice skipped. It feels fair after a good month, and the hard call goes unrehearsed. - The Mediocre ApproachThe poor outcome
 Nurse:Any new surgery date needs the surgeon’s okay first.Scheduler:I just gave her the first opening.Scheduler (thinking):Now she gets a second call.
The next week, the real call. A surgery day has been cancelled, and nobody practiced. The scheduler gave the patient the first open date before the surgeon approved the timing, so now the patient gets a second call. Rewind. Same team, same request, same moment. This time, the practice happens.
- The Exceptional ApproachThe action: keep the time
 Front-desk lead:Catch-up gets an hour Friday. I’ll play the patient.Scheduler:I’m so sorry. We need to move your date.
The shares hold. Catch-up gets its own hour on Friday, and the 24 minutes go to the call: an apology, a plain reason, and the surgeon’s okay before any new date. - The Exceptional ApproachThe exceptional outcome
 Scheduler:I’m so sorry. We need to move your surgery date.Scheduler:Our surgeon checks the timing first. Then I’ll call you back.Patient (on the phone):Okay. Thank you for telling me straight.
The next week, the real call. The words are ready. She apologizes, explains that the surgeon checks the timing first, and says she will call back with the new date.
Example TwoAt a glance
The ProblemThe team hour has just started. Its first 24 minutes are for practicing the call that tells a patient a surgery date has to move. After a smooth month, a scheduler asks to skip the role-play.
The Mediocre ApproachSkip practice in a good month
Action
Use the time for catch-up.
- “Fair enough. We know this stuff”
- The hard call goes unrehearsed
Poor outcome
No words when it counts.
- The next week, the patient gets the first open date before the surgeon approves the timing
- The nurse has to stop it, and the patient gets a second call
The Exceptional ApproachThe share kept: practice first
Action
Keep the 24 minutes.
- Catch-up gets its own hour on Friday
- In pairs, they rehearse the apology, the reason and the surgeon’s okay before new dates
Exceptional outcome
Ready for the real call.
- The next week, the scheduler apologizes and gives the plain reason
- She explains that the surgeon checks the timing first, and says she will call back with the new date
Your clinic
More Ways to Use the Hour
Same pattern every time: a share decided ahead, one named owner, and the hour kept.
| What comes up | Who answers, and how | Settled before the month ends |
|---|---|---|
| Practice share: an emergency in the procedure room is rare, so nobody remembers who does what | The nurse leads a walk-through of the clinic’s written emergency protocol at the procedure chair, with the Mohs surgeon: who calls, who positions the patient, who brings supplies, and when to call emergency services | Everyone has walked their role, and any missing supply has an owner and a date |
| Practice share: the front desk dreads calls from patients confused by a bill after surgery | The billing lead plays the caller; the front desk practices the opening line and the handoff to billing | Everyone knows the words, and which questions go straight to billing |
| Fix share: two pathology reports sat unrouted for days because the covering-clinician field was blank | Records staff tell the responsible clinician the same day; the clinician reviews both reports and makes sure both patients are told | In the hour, the team agrees on the lasting fix, such as a required covering-clinician field, with the medical director’s sign-off, an owner and a start date |
| Idea share: a scheduler suggests a text telling Mohs patients what to bring and how long the day may last | The practice manager logs it and settles the logistics; a clinician signs off any wording about eating, medications or preparation | Next month’s idea share opens with the answer: yes, not now, or no, and why |
| The block: the hour has been cancelled three months running for overbooked clinics | The practice manager and the lead physician switch to a standing 30 minutes every other week, at the same time | The block sits in the schedule template like a patient appointment, paid for every role |
Adapt the shares, the topics and the owners to your own team. Anything clinical still goes to a clinician.
Your move
Try It Today
Split it. Post it. Keep it.
Try it for one month, with one hour. No new software and no committee.
- Block one hour. Today, the practice manager blocks one paid team hour next month in the scheduling system, before booking opens.
- Split it and post it. Write the three shares on one page: 24 minutes of practice, 18 minutes to fix one process, 18 minutes for one staff idea.
- Pick the three topics. One hard moment to rehearse, one process that failed this month, and one question that invites staff ideas.
- Agree on one rule. The lead physician and the practice manager agree: only the practice manager moves the hour, and only to another slot in the same month.
- Run it with a timer. When a share’s time is up, move on. End by naming one owner and one date for the fix, and book next month’s hour before anyone leaves.
Anything urgent still goes straight to the clinician.
A full schedule asks for every hour that isn’t already promised. Promise the hour first, then keep it, in good months too.
Explore the Evidence
19 sources · what each source is, what it found, what it supports here, and its limits
This chapter uses only the claims an independent reviewer accepted in a scoped review of the research package (38 of 61 claim rows; the rest are outside that review, not shown false). The Singapore Airlines story on this page is assembled from separate sources, each used for what it shows. The 40-30-30 rule rests on a few sentences from one unnamed senior manager in charge of staff development, quoted in a teaching case by Wirtz and Heracleous (reference 2). The case is copyrighted 2016 and was revised in 2021. It draws on publications from 2008 to 2010 and interviews from 2015, and gives no date for the statement, so it may predate 2016. No other primary statement of the rule was found in the sources opened for this research. The case does not say whether the shares measured money, hours or attention, over what period, or for which part of the airline, and it reports no audit of the rule. It does not say whether the shares were set in advance. The same case says, separately, that nearly half of the airline’s spending goes to job-skills training and retraining, a second undefined figure that does not match 40%. So the page teaches the rule as one manager’s description, never as what the airline spends, and it is not a measured or optimal ratio or a proven cause of the airline’s results. Deciding the split before the month starts, the clinic hour and its 24, 18 and 18 minutes are this chapter’s own design, drawn from the manager’s proportions and from the capability-trap research. The design is an untested proposal. It has not been tried in clinics, and urgent patient care always comes first. The 15-week course is the teaching case’s description, and its authors rank it as the industry’s longest and most thorough without giving comparison data; it is not given here as today’s requirement. Former chief executive Cheong Choong Kong’s words are quoted in the case without a date. Chief executive Goh Choon Phong is also quoted there saying the airline will keep investing heavily in training even in the hardest times; no spending figure tests that pledge. The 76 and 85 training hours (reference 4) are company figures for Singapore Airlines and Scoot for the financial year ending 31 March 2026, with 21,667 employees at year end; the average is total training hours divided by employees on 31 March, and the group did not seek external assurance for the report. The hours rise and fall: the overall average was 80, 67 and 76 over the last three years, cabin crew averaged 59, 81, 109, 80 and 85 over five years, and hours for managers and above fell from 36 to 25 in the last year. From this year Scoot counts crew training hours by a new method, so the latest year is not like-for-like. The same report gives a learning-and-development investment printed only as “$68 million”; the currency is not converted here. SPARK Time is reported for Scoot’s office staff only, with no start date, attendance or results. The staff-ideas figures (reference 3) describe the group in 2007-08, a period that spans two years: the source says “nearly 5,948” ideas, rounded here to nearly 6,000, and names cutting costs and improving efficiency as the scheme’s focus, not service. That every idea was evaluated is the case study’s report; telling each person what happened to their idea is this chapter’s proposed clinic practice. The academic account of the airline is interview-based research on one company, 31 interviews and site visits from 2001 to 2011, with no comparison group, by authors with a long engagement with the airline. Counterevidence from the employee side is real. The teaching case says the airline pays about average for Singapore and below the global level, and records disputes with unions, including a 2007 pilot pay dispute over the A380 that went to the Industrial Arbitration Court. Its own study questions note that five-year renewable crew contracts would meet disapproval in the US and Europe, and ask how staff feel in a culture focused intensely on customers while cutting internal costs; the 2026 careers page still offers new crew an initial five-year contract (reference 19). In the pandemic year to 31 March 2021, the group reported a net loss of S$4,271 million. A hiring freeze, early retirement, voluntary release and unpaid leave removed around 1,900 positions without job cuts; after 4,300 positions were announced for cutting, the final number of involuntary job losses was about 2,000 (reference 17). That figure is not the whole fall in headcount. The mechanism is a model, not a trial. Repenning and Sterman (reference 1) built a system-dynamics model from field studies; their DuPont figures are a 1991 benchmark, and the worse-before-better step is the improvement team’s model conclusion, not an observed result. Their DuPont account also shows protected improvement effort being cut back after it succeeded, which is why the page says to keep the time in good months. Perlow’s quiet-time study (reference 5) followed one software team in the 1990s, with productivity rated by the engineers themselves and no control group; the gain faded within months. Tucker and Edmondson (reference 6) and Tucker and Spear (reference 11) observed nurses in US hospitals; Tucker and Spear recommend improvement triggered by failures, and a fixed monthly fix-it share is this page’s design, not theirs. The training reviews (references 7 and 10) pool many different programs. The simulation review studied health-profession trainees using technology-enhanced simulation against no training, so applying it to role-play in a team hour is an analogy, and its effect on patients was smaller than its effect on skills. The protected-learning reviews (references 15 and 16) give recommendations and mechanisms, not measured outcomes. The Welsh pharmacy pilot (reference 8) reported benefits, and also rising costs for locum cover and disruption to services: protected time costs money and capacity. The in-clinic rehearsal studies (references 9, 12, 13 and 14) are small, uncontrolled, mostly self-reported and read as abstracts; they measured staff knowledge and confidence and the safety concerns or process gaps the rehearsals found, not adverse events for patients, in dermatology or anywhere else. No source here tested a split of team time in a dermatology clinic. The two clinic examples, the extra ideas and the one-month experiment are illustrations of the mechanism, written for this chapter with fictional people, not observed events, tested interventions or approved clinical protocols. The two comic strips are illustrations too. The pump room is an invented composite that shows the capability trap; it is not DuPont or any real plant. The airline scenes are invented, unbranded rooms with invented people, sketching the three shares the manager described; they are not observed Singapore Airlines events, and their percentages repeat her description, not a measured budget. Status shows how each source was read: HTML (web page), ABS (abstract) or FULL (full text, or the named sections of a long report).
| Source | Type and context | Key finding | What it supports here | Material limitation |
|---|---|---|---|---|
| [1] · FULLRepenning NP, Sterman JD. Nobody ever gets credit for fixing problems that never happened. Calif Manage Rev 2001 | Management research A system-dynamics model built from field studies of improvement programs in US manufacturing, product development and other firms | Improvement gives more lasting gains than working harder but pays off only after a delay, so under pressure organizations cut it and fall into a self-reinforcing capability trap; successful improvement programs were the exception in their study; DuPont’s 1991 benchmark found 10-30% higher maintenance spending for each dollar of plant value and uptime some 10-15% lower; after the maintenance program’s gains, a team member warned that people would be taken away once problems fell, and mandated cost-cutting then brought downsizing that weakened the program | The problem (section 1), the summary, the source comparison and mechanism cards 1 and 5 | A conceptual model with examples the authors chose, not a controlled trial and not a test of any fixed split of time; the worse-before-better step at DuPont is the improvement team’s model conclusion, not an observed result; the later erosion at DuPont is counterevidence that protected improvement effort is easily lost after it succeeds |
| [2] · FULLWirtz J, Heracleous L. Singapore Airlines: Managing Human Resources for Cost-Effective Service Excellence. Teaching case, 2016, revised 2021 | Academic teaching case A business-school case built mostly on company voices quoted by the researchers | An unnamed senior manager in charge of staff development describes a 40-30-30 rule inside the Transforming Customer Service program, which spanned five operational areas: 40% of resources to training people, 30% to reviewing processes, and 30% to new products and services; new cabin crew start with a 15-week course, which the authors rank as the industry’s longest and most thorough; former chief executive Cheong Choong Kong says training never ends at the company; the case also puts nearly half of the airline’s spending on job-skills training and retraining, and lists five parts of its human-resources strategy, including heavy investment in training | The rule, its three shares and the program (summary, section 2, the comparison and mechanism cards 2 to 4), the 15-week course and the former chief executive’s words | One unnamed manager’s undated statement, which may predate 2016; the unit of the shares is not defined, and scope and period are not stated; the case reports no audit; the case does not say whether the shares were set in advance; the second figure, nearly half of spending, is also undefined; the superlative about the course is the authors’ own, with no comparison data, and the 15-week figure is not a current requirement; pay is about average by Singapore standards, union disputes are recorded, and the case’s own study questions raise five-year crew contracts and how staff feel |
| [3] · FULLHeracleous L, Wirtz J. Singapore Airlines: achieving sustainable advantage through mastering paradox. J Appl Behav Sci 2014 | Peer-reviewed qualitative case study 31 in-depth interviews with managers at senior and middle levels and with cabin crew, and repeated site visits, 2001-2011 | In 2007-08, staff across the group put nearly 5,948 ideas into the Staff Ideas in Action scheme; the case study reports that every idea was evaluated and over 40% were implemented; the scheme had been running for nearly 30 years, focused on cutting costs and improving efficiency; a small central product innovation department, staffed by people who rotate through every two to three years, works alongside continuous improvement run and funded by individual departments | The idea share and the process share (summary, section 2), mechanism cards 3 and 4, results card 2 | Single-firm qualitative research without a comparison group, by authors with a long engagement with the airline; the figures describe 2007-08 and the 2001-2011 study period; “nearly 6,000” on the page rounds the source’s “nearly 5,948”; the scheme’s stated focus is costs and efficiency, not service; selected sections read |
| [4] · FULLSingapore Airlines. Sustainability Report FY2025/26. 25 June 2026 | Company sustainability report Singapore Airlines and Scoot, financial year 2025/26 (April 2025 to March 2026) | An average of 76 hours of training for each employee (cabin crew 85) and $68 million reported for learning and development; 21,667 employees at 31 March 2026; overall averages of 80, 67 and 76 hours over the last three years, five-year cabin crew averages of 59, 81, 109, 80 and 85, managers and above 36 then 25; Scoot’s SPARK Time gives its office staff a standing two-hour block on Thursdays for learning on their own, sharing knowledge and talking with leaders; no external assurance sought | Training hours (summary, section 2, results card 1) and the weekly block (summary, section 2, results card 3) | Company self-report, not externally assured; the average is total hours divided by employees on 31 March; hours rise and fall from year to year, and from FY2025/26 Scoot counts crew training hours by a new method, so years are not like-for-like; the currency is printed only as “$” and is not converted here; SPARK Time is for Scoot office staff, with no start date, uptake or outcomes reported; relevant pages read, not the whole report |
| [5] · FULLPerlow LA. The time famine: toward a sociology of work time. Adm Sci Q 1999 | Qualitative field study Nine months with a 17-person software team in one US firm, with quiet time (blocks without interruptions) three mornings a week | The share of engineers rating their own productivity above average rose to 59% and then 65%; when the researcher returned months later, little of the effect remained and the engineers were back in their old work patterns; a later attempt by managers to bring quiet time back failed | Keeping protected time (summary, mechanism card 5) | One team in the 1990s; productivity was self-rated on a five-point scale; no control group; the researcher’s presence may have sustained the policy; Perlow concludes such changes last only if the underlying work-time habits also change; selected pages read |
| [6] · FULLTucker AL, Edmondson AC. Why hospitals don’t learn from failures. Calif Manage Rev 2003 | Qualitative observational field study 26 nurses at nine US hospitals, observed for 239 hours | For 93% of problems, nurses did what it took to continue care without addressing the cause; only 7% of responses met lenient criteria for root-cause problem solving; the authors tie this partly to staffing designed without slack time | The problem (section 1), the source comparison and mechanism card 3 | Nurses only, with data collected around 1999-2000; qualitative coding of 194 observed failures; it describes a pattern and does not test protected time; selected pages read |
| [7] · ABSArthur W Jr, Bennett W Jr, Edens PS, Bell ST. Effectiveness of training in organizations: a meta-analysis of design and evaluation features. J Appl Psychol 2003 | Meta-analysis Studies of organizational training | Sample-weighted mean effect sizes of about 0.60 to 0.63 across reaction, learning, behavior and results; for behavior, d = 0.62 across 122 studies and 15,627 people; the authors call this a medium to large effect | Mechanism card 2 (training changes what people do) | Read as the abstract; not specific to health care; many different training programs are pooled |
| [8] · ABSBartlett S, Bullock A. Protected learning time in community pharmacy and possibilities for upscaling: an exploratory study in Wales, UK. J Pharm Policy Pract 2026 | Qualitative realist evaluation of a pilot Wales; a funded pilot of 12-15 days of protected learning time for community pharmacists; diaries from 20 pharmacists, 15 interviews, 12 employer surveys and 3 education leads (30 participants) | Participants reported benefits for development, wellbeing and services; employers commonly faced challenges, including higher costs for locum cover and disrupted services; participants suggested pre-scheduled slots or hours away from patients | Where else it works (section 4): booking protected time ahead | Read as the abstract; self-report; counterevidence on cost: protected time costs money and can disrupt services and patients’ access, even where staff value it |
| [9] · ABSLaVelle BA, McLaughlin JJ. Simulation-based education improves patient safety in ambulatory care. In: Advances in Patient Safety, Vol. 3. AHRQ, 2008 | Program report In-situ simulation of chest pain and anaphylaxis across 21 primary or specialty clinics and five urgent-care clinics in one US health system, 2008 | Reported gains in staff knowledge, confidence and skills; the simulations uncovered 40 safety concerns that were then addressed | Results card 5 (rehearsal in the real clinic turns up fixes) | Read as the abstract; the program authors’ own evaluation, with no control group; it does not show fewer actual adverse events for patients |
| [10] · ABSCook DA, Hatala R, Brydges R, et al. Technology-enhanced simulation for health professions education: a systematic review and meta-analysis. JAMA 2011 | Systematic review and meta-analysis 609 studies with 35,226 health-profession trainees; simulation compared with no intervention | Pooled effect sizes of 1.09 for process skills and 0.50 for direct effects on patients, with large heterogeneity; 137 randomized, 67 nonrandomized two-group and 405 single-group pretest-posttest studies | Results card 4 (rehearsal builds skill) | Read as the abstract; technology-enhanced simulation, so applying it to low-tech role-play in a team hour is an analogy; large heterogeneity and many single-group designs; searches through May 2011 |
| [11] · ABSTucker AL, Spear SJ. Operational failures and interruptions in hospital nursing. Health Serv Res 2006 | Descriptive observational study 11 nurses observed in six US hospitals, with surveys in 48 units | 8.4 work-system failures in an average 8-hour shift, 6.4 of them involving medications, supplies, orders, equipment or staffing; average task time 3.1 minutes and eight mid-task interruptions per shift; the authors suggest improvement processes triggered by failures | The clinic’s own rush (section 5) | Read as the abstract; a small observed sample; the authors recommend failure-triggered improvement, and a fixed monthly fix-it share is this page’s own design, not their recommendation |
| [12] · ABSCopaescu AM, Graham F, Nadon N, et al. Simulation-based education to improve management of refractory anaphylaxis in an allergy clinic. Allergy Asthma Clin Immunol 2023 | Uncontrolled mixed-methods study Canada; in-situ anaphylaxis simulation in an allergy clinic, 17 participants | Participants reported improvement; the simulation exposed gaps in the clinic’s process, which were later resolved | The practice share (section 5) | Read as the abstract; small single-site sample; self-report and interviews; no patient-outcome measures |
| [13] · ABSCovington CC, Muckler VC, Sheldon L, Alexander R, Morgan B. Improving emergency airway knowledge and self-efficacy levels of outpatient gastroenterology staff. Gastroenterol Nurs 2019 | Uncontrolled pre-post project US outpatient endoscopy staff; online education and in-situ simulation | Gains in staff knowledge and self-efficacy at 6 weeks and 3 months | The practice share (section 5) | Read as the abstract; the sample size is not stated in the abstract; self-efficacy is self-reported; no patient-outcome measures |
| [14] · ABSWarshafsky C, Singh SS, Garber AB. In-situ simulation for enhancing safety in outpatient hysteroscopy. MedEdPORTAL 2026 | Uncontrolled pre-post evaluation Four outpatient complication scenarios, including a vasovagal reaction; 12 participants | Participants reported improved confidence in managing complications | The practice share (section 5) | Read as the abstract; small sample; self-reported confidence; no patient-outcome measures |
| [15] · ABSMertens F, de Groot E, Meijer L, et al. Workplace learning through collaboration in primary healthcare: a BEME realist review. Med Teach 2018 | Realist systematic review 42 publications from 6,930 references; primary care, mainly general practitioners and nurses; literature from 1990 to 2015 | Recommends that policy makers and managers make sure professionals can use protected time set aside for learning | Evidence only (context for protected learning time); not cited in the teaching text | Read as the abstract; a recommendation drawn from mostly qualitative and mixed studies, not a test of protected time with measured outcomes |
| [16] · ABSSholl S, Ajjawi R, Allbutt H, et al. Balancing health care education and patient care in the UK workplace: a realist synthesis. Med Educ 2017 | Realist synthesis UK literature from 1998, across health professions | Protected learning time was among the most common interventions; interventions worked mostly through organizational funding, workload management and support | Evidence only (context for the paid, managed clinic hour); not cited in the teaching text | Read as the abstract; outcome measures are not given in the abstract |
| [17] · FULLSingapore Airlines. Annual Report FY2020/21. 2021 | Company annual report Group account for the year to 31 March 2021, in Singapore dollars; named pages of a keyword-searched report | A net loss of S$4,271 million; a recruitment freeze from March 2020, early retirement, voluntary release for cabin crew and voluntary no-pay leave reduced headcount by around 1,900 positions without job cuts; after a September 2020 announcement of 4,300 positions to be cut, the final number of involuntary job losses was about 2,000; salary cuts began with management and were extended to all employees | Evidence only (counterevidence); not cited in the teaching text | Company self-report; the roughly 2,000 figure counts involuntary job losses only, not the whole fall in headcount, and the report does not reconcile its figures with its year-end staff table; no training-spending figure was found, so the chief executive’s pledge in the teaching case to keep investing in training in difficult times is not tested by data2 |
| [18] · FULLTransport Safety Investigation Bureau, Singapore. Final Report: B777-300ER, 9V-SWM, turbulence event over Myanmar, 21 May 2024. 18 May 2026 | State accident-investigation final report Investigation delegated to Singapore’s bureau by Myanmar under international accident-investigation rules; front matter, synopsis, conclusions, safety actions and recommendations read | Flight SQ321 was classified as an accident; the aircraft met severe convective turbulence, and the bureau could not rule out that the weather radar intermittently showed it weakly or not at all; afterward the airline ran weather-radar refresher training for all flight crews (July to December 2024), turbulence e-learning for flight and cabin crew, reinforced scenario-based turbulence training for cabin crew, a workshop for trainee cabin crew, more seat-belt reminders and announcements, and radar guidance and defect reporting | Evidence only (counterevidence and context); not cited in the teaching text | Training and procedure changes made in response to an accident: event-triggered learning that neither shows nor disproves a pre-set share for training or process review; the findings concern weather, radar behavior and seat-belt use, not training allocation; the bureau’s reports do not assign blame or liability; no measure of the actions’ effect is given; the factual and analysis sections were skimmed only |
| [19] · HTMLSingapore Airlines. Cabin Crew careers page (Singapore). Accessed 10 November 2026 | Company careers page An undated recruitment page | New crew are based in Singapore on an initial contract of five years, which can be extended depending on performance | Evidence only (counterevidence); not cited in the teaching text | Shows that the contract model the teaching case’s own study questions say would meet disapproval in the US and Europe is still current2; a recruitment page, undated |
References
- Repenning NP, Sterman JD. Nobody ever gets credit for fixing problems that never happened: creating and sustaining process improvement. Calif Manage Rev. 2001;43(4):64–88. web.mit.edu
- Wirtz J, Heracleous L. Singapore Airlines: managing human resources for cost-effective service excellence. Case 11. Teaching case, © 2016, revised 2021. jochenwirtz.com
- Heracleous L, Wirtz J. Singapore Airlines: achieving sustainable advantage through mastering paradox. J Appl Behav Sci. 2014;50(2):150–170. doi.org/10.1177/0021886314522323 · NUS Business School copy
- Singapore Airlines. Sustainability Report FY2025/26. 25 June 2026. links.sgx.com
- Perlow LA. The time famine: toward a sociology of work time. Adm Sci Q. 1999;44(1):57–81. web.mit.edu
- Tucker AL, Edmondson AC. Why hospitals don’t learn from failures: organizational and psychological dynamics that inhibit system change. Calif Manage Rev. 2003;45(2):55–72. utsouthwestern.edu
- Arthur W Jr, Bennett W Jr, Edens PS, Bell ST. Effectiveness of training in organizations: a meta-analysis of design and evaluation features. J Appl Psychol. 2003;88(2):234–245. doi.org/10.1037/0021-9010.88.2.234 · PubMed 12731707
- Bartlett S, Bullock A. Protected learning time in community pharmacy and possibilities for upscaling: an exploratory study in Wales, UK. J Pharm Policy Pract. 2026;19(1):2629063. PubMed 41736965
- LaVelle BA, McLaughlin JJ. Simulation-based education improves patient safety in ambulatory care. In: Advances in Patient Safety: New Directions and Alternative Approaches, Vol. 3. Agency for Healthcare Research and Quality; 2008. PubMed 21249927
- Cook DA, Hatala R, Brydges R, et al. Technology-enhanced simulation for health professions education: a systematic review and meta-analysis. JAMA. 2011;306(9):978–988. doi.org/10.1001/jama.2011.1234 · PubMed 21900138
- Tucker AL, Spear SJ. Operational failures and interruptions in hospital nursing. Health Serv Res. 2006;41(3 Pt 1):643–662. doi.org/10.1111/j.1475-6773.2006.00502.x · PubMed 16704505
- Copaescu AM, Graham F, Nadon N, et al. Simulation-based education to improve management of refractory anaphylaxis in an allergy clinic. Allergy Asthma Clin Immunol. 2023;19(1):9. PubMed 36710363
- Covington CC, Muckler VC, Sheldon L, Alexander R, Morgan B. Improving emergency airway knowledge and self-efficacy levels of outpatient gastroenterology staff via implementation of online education and in situ simulation. Gastroenterol Nurs. 2019;42(3):242–250. PubMed 31145248
- Warshafsky C, Singh SS, Garber AB. In-situ simulation for enhancing safety in outpatient hysteroscopy: development and evaluation of a crisis resource management-based training package. MedEdPORTAL. 2026;22:11604. PubMed 42253339
- Mertens F, de Groot E, Meijer L, et al. Workplace learning through collaboration in primary healthcare: a BEME realist review of what works, for whom and in what circumstances. BEME Guide No. 46. Med Teach. 2018;40(2):117–134. PubMed 29094626
- Sholl S, Ajjawi R, Allbutt H, et al. Balancing health care education and patient care in the UK workplace: a realist synthesis. Med Educ. 2017;51(8):787–801. PubMed 28429527
- Singapore Airlines. Annual Report FY2020/21. 2021. singaporeair.com
- Transport Safety Investigation Bureau, Ministry of Transport, Singapore. Final Report: B777-300ER, 9V-SWM, Turbulence Event over Myanmar, 21 May 2024. TIB/AAI/CAS.231. 18 May 2026. icao.int copy
- Singapore Airlines. Cabin Crew (careers page, Singapore). Undated; accessed 10 November 2026. singaporeair.com/careers
Explore the evidence · Try it today · Read the Singapore Airlines Daily Brief · More lessons from The Exceptional Private Practice